
Ending a bath trip
Stopping a bad trip with medication is sometimes possible, but medication is not the first step that should be taken immediately. In many cases, it works better to first provide peace, safety, and good guidance during a difficult or anxious psychedelic experience. A calm guide, a safe environment, fewer stimuli, reassurance, a different body posture, appropriate music, and supportive presence can all do a lot. Sometimes it also helps to provide some physical stability, for example with some dextrose and GABA. Taking these medications can often provide just that bit of peace so that the bad trip turns into more peace. Therefore, not every difficult trip needs to be stopped immediately with medication.
That makes sense, because a challenging start to a trip doesn’t have to go wrong. In the beginning, tension, fear, or confusion can sometimes be part of a process in which old tension is touched upon. If a sense of breakthrough, relief, or victory follows afterwards, such a difficult start can even turn out to be very valuable. A difficult phase therefore doesn’t necessarily mean that the session is a failure or dangerous. Often, the difference lies in the level of guidance, adaptability, and whether someone remains accessible and safe.
Why a trip can be challenging, especially the beginning
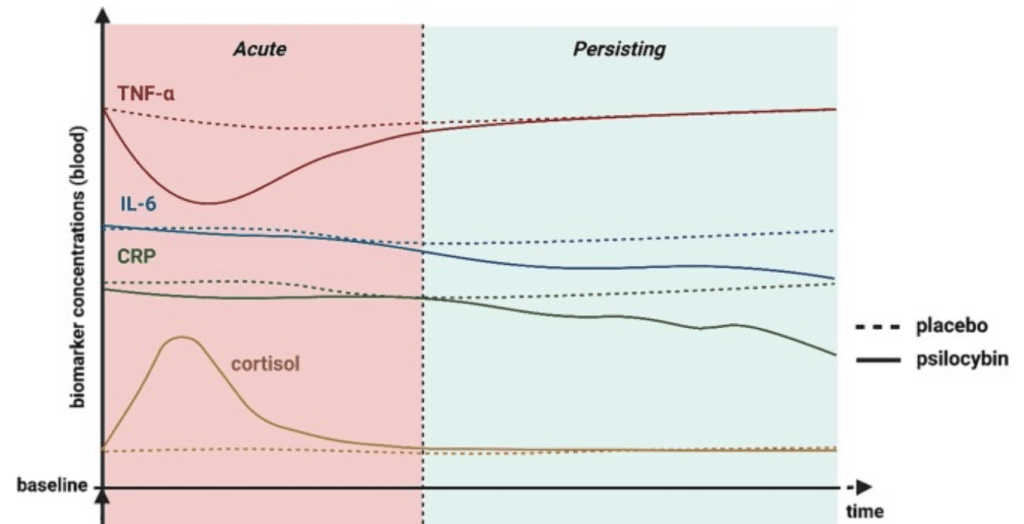
A trip can feel challenging because there is a lot of change happening in the body and mind in a short period of time. Biologically, with various psychedelics, including psilocybin, you often first see an increase in cortisol, as can be seen in the image. Cortisol is a stress hormone and can temporarily cause restlessness, tension, or a sense of alertness, but this usually decreases again as the experience unfolds. At the same time, glutamate is also affected, an important signaling molecule involved in processing stimuli, learning, and brain activity, which can make thoughts more intense, associative, or less predictable. This makes the beginning of a trip sometimes feel physically restless or mentally overwhelming, even without there being anything immediately wrong.
In addition, emotions that normally remain in the background can emerge; while people often have a natural resistance to truly allowing sadness, fear, shame, or old tensions to emerge. Time control, self-perception, and reality can also become less stable, partly because the activity of the default mode network, the DMN, decreases. This network normally helps to maintain a stable narrative about oneself and the world. When it becomes temporarily looser, this can be liberating, but it can also be confusing or exciting at first. Furthermore, the experience is often new, and people naturally resist the unknown. A challenging trip is therefore often a temporary combination of biological activation, emotional release, reduced control, and entering unfamiliar inner terrain. A challenging trip is therefore often a temporary combination of biological activation, emotional release, reduced control, and entering unfamiliar inner terrain.
These disruptive effects mainly occur during the initial phase of the trip. If people have too much resistance or want to cling too tightly to the familiar, this can lead to an challenging start. If the resistance persists throughout the trip, it becomes called a bad trip.
When medication becomes an option
Medication only really comes into play when non-medication support is insufficient, or when the situation threatens to become unsafe. Think of severe panic, disorientation, dangerous behavior, persistent agitation, or completely losing contact with the psychedelic facilitator. Then the goal is no longer to help someone get through the difficult phase, but to reduce the intensity or actually break the psychedelic state.
There is an important distinction between means that primarily calm someone down and means that in themselves materially reduce the psychedelic effect. This distinction is often not made sufficiently in the literature. Making someone calmer is not the same as actually stopping the trip.
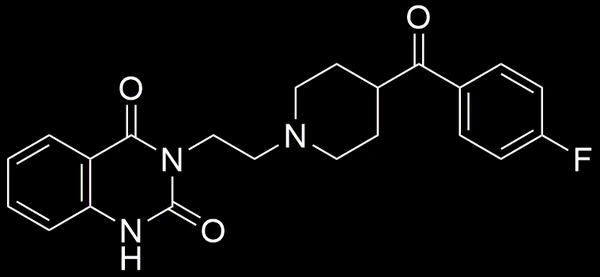
The best real trip stopper is ketanserine
If the goal is truly to chemically stop a classic serotonergic trip, such as that of LSD, psilocybin, DMT or mescaline, ketanserine emerges as the strongest candidate. The reason is that ketanserine blocks the 5-HT2A receptor, and that is precisely the most important receptor through which classic psychedelics cause their characteristic effects. Therefore, ketanserine is not only a sedative, but a means that can slow down the core of the trip.
According to This study shows ketanserine to be the best real trip stopper. The disadvantage is mainly that it is not readily available everywhere and that it can lower blood pressure. Still, from a pharmacological perspective, this is the most direct choice if one wants to purposefully end a classic psychedelic state.
Risperidone is the best practical alternative
Because ketanserine is not always available in practice, risperidone is often considered the best practical alternative. In the Netherlands, risperidone is more well-known, more readily available, and more familiar to doctors as a treatment for acute psychiatric situations. Risperidone also has a strong effect on the 5-HT2A receptor and can therefore do more than just sedate.
If ketanserin is not available, risperidone is probably the most logical pharmacological option to attenuate a bad trip. That does not necessarily make risperidone pharmacologically better than ketanserin, but it is often more realistically applicable.
Not every trip stopper actually stops the trip.
There are also other drugs that are sometimes used, such as olanzapine, quetiapine, trazodon, mirtazapine or the benzodiazepines like diazepam and lorazepam. These can be useful in certain situations, but not all of them have the same function. Benzodiazepines mainly reduce anxiety and tension and can make someone calmer, but they usually do not really stop the psychedelic experience. Quetiapine is also often mentioned by users, but that seems partly due to the fact that it acts sedatively. Sedation is not the same as receptor-targeted trip-killers.
Someone can become more drowsy and calm by taking various medications, but still remain in the psychedelic state. If the goal is really to end the trip itself, ketanserine and risperidone are much more logical means than just a sedative.
Why conditions must first be adjusted
In practice, many bad trips do not arise solely from the substance, but also from the combination of tension, expectation, environment, and a lack of support. That is why adjusting the setting can often have a surprisingly big effect. Other music, less light, fewer people in the room, a familiar voice, more physical relaxation, and reducing cognitive overload can often bring someone back to a more safe state. Sometimes it also helps to support the body with a little sugar + GABA or a soothing protocol, as long as that is done carefully and within the guidance.
In guided sessions, this is often the first and best option. Many people who seem to panic still manage to get through the difficult phase when they feel safe again. What at first seemed like a breakdown turns out to have been an intense but meaningful part of the session afterwards.
A difficult trip is not always a bad trip
That might be the most important nuance. A journey can start confrontingly, chaotically, or emotionally intense, yet end up being healing. Especially when someone moves through fear and then experiences relief, insight, or a sense of victory, the session can actually yield a lot. You see this more often when the guidance is good and the person is not rushed out of the process.
Medication should therefore not be used out of haste or out of discomfort from the environment. It should be a means for situations where safety or stability are truly at risk, not for every difficult emotion or every challenging phase. Sometimes the art is actually to help someone stay well rather than immediately stop.
Also pay attention to the preparation and neurochemistry
You cannot prevent a bad trip with just the right dose or a good guide; it is primarily about proper preparation. Many difficult experiences do not arise purely from the substance itself, but from the combination of tension, uncertainty, physical discomfort, hidden emotions, and an environment that does not adequately meet a person’s needs. Preparation helps to reduce those risk factors even before the session begins. If someone knows what can happen biologically and psychologically, anxiety, emotional waves, or distortion of time and self-perception are less likely to be perceived as a danger. That alone can make a big difference in reducing panic.
When preparing for the Triptherapie match, we also pay special attention to neurochemistry. Research has shown that Relatively high levels of glutamate and low levels of GABA can be an important factor in negative experiences.. Glutamate is associated with irritability, mental activity, and sometimes a feeling of being driven or overstimulated, whereas GABA supports more calmness, inhibition, and stability. If someone already feels tense, poorly rested, or has a neurochemical imbalance when they begin a session, a psychedelic experience can be experienced as too intense or threatening more quickly. That is why we pay attention to things like sleep, stress levels, diet, supplements, medication, stimulants, and the overall stress load of the nervous system.
Good preparation also means that you look ahead to intention, mental strain, physical condition, medication use, sleep, and diet beforehand. Additionally, it helps to discuss beforehand how you will deal with fear, loss of control, or emerging emotions. Who learns beforehand that resistance often adds more tension and surrender can actually create space, will have more grip during the trip. Preparation therefore does not ensure that a session will always be easy, but rather that difficult moments will be less likely to turn into a real bad trip.
Conclusion
Stopping a drug trip with medication can sometimes be necessary, but good guidance remains always the most important first step. Rest, safety, appropriate music, reassurance, fewer stimuli and bodily regulation can already do a lot, and sometimes even a difficult start can still turn into a valuable experience if relief, insight or a sense of victory follows afterwards. Therefore, not every challenging trip is a failed trip, and that is precisely why medication should not be used too quickly.
If medical intervention is still necessary, the literature discussed mainly shows ketanserine to be the best real trip stopper, with risperidone as the best practical alternative when ketanserine is not available. These drugs are more logical than only sedative drugs because they act more strongly on the mechanism of action of classic psychedelics. At the same time, this topic also shows how important preparation is. Therefore, when Triptherapie looking at it, we do not only consider the dose and setting, but also factors such as stress, sleep, medication, emotional stress, and neurochemical balance, whereby a state of relatively high glutamate and low GABA can increase the risk of a negative experience. The best protection against a bad trip therefore does not begin with a trip stopper, but with careful preparation, good guidance and only then, if really necessary, the right medication.
Disclaimer
The information in this article about stopping a psychedelic experience with drugs such as ketanserin or risperidone is based on theoretical and pharmacological insights. Please note the following:
Only through a doctor: These medications are governed by the Medicines Act and may only be prescribed and administered by a qualified physician. Self-mixing psychedelics with these heavy medications can be dangerous.
Current practice vs. theory: Although ketanserine and risperidone are theoretically the most effective ’trip-killers’ because they act directly on serotonin receptors, they are still rarely used for this specific purpose in current medical practice.
Current emergency procedures: In acute emergency situations (such as extreme panic or a bad trip at the emergency room), benzodiazepines (such as diazepam or lorazepam) are currently being used more frequently. These drugs do not stop the trip itself, but they work by calming and reducing anxiety to make the situation manageable.
Future prospects: As psychedelic therapy becomes more standardized and more frequently used in medical settings, it is possible that specific receptor blockers such as ketanserine will play a greater role in the future.
So: Always rely first on good guidance, a safe environment, and techniques that help with relaxation when facing a difficult experience. Always seek professional help for medical concerns and never experiment with prescription medication on your own.